

The Department of Health and Human Services (HHS) has officially finalized comprehensive revisions to its regulations implementing Title VI of the Civil Rights Act of 1964. Finalized on July 23, 2026, the updated rule formally eliminates disparate impact as a valid legal basis for determining whether unlawful discrimination has occurred within any programs, services, or activities that receive federal financial assistance from HHS.
This major regulatory overhaul was issued in direct response to Executive Order 14281, titled "Restoring Equality of Opportunity and Meritocracy," which was enacted to realign federal civil rights oversight with strict interpretations of statutory text. The action mirrors similar policy shifts implemented across multiple federal bodies, including coordinated rulemakings and regulatory rollbacks by the Department of Justice (DOJ), the Department of Education (DOE), and the Department of Housing and Urban Development (HUD).
By narrowing the scope of administrative enforcement, the newly finalized rule marks a profound pivot in the federal government’s five-decade-old approach to safeguarding civil rights. Legal experts and public health analysts note that the changes could allow facially neutral institutional policies—those that inadvertently create stark disparities in health care access and medical outcomes—to remain unaddressed by federal administrative investigators unless direct evidence of intentional bias can be proven.
To understand the weight of this regulatory transformation, it is necessary to examine the foundational history of Title VI. Enacted during the peak of the Civil Rights Movement in 1964, Title VI established a federal statutory prohibition against discrimination based on race, color, or national origin in any program or activity receiving federal funds. Historically, this legislation served as a vital corrective mechanism against widespread, systemic discrimination by institutions receiving federal dollars. During that era, many hospitals and medical facilities openly refused to treat Black patients, maintained strictly segregated wards and waiting rooms, or provided categorically unequal standards of care. Over the decades, Title VI evolved into a cornerstone of civil rights enforcement across health care, education, and social services.
While the text of the statute itself and subsequent Supreme Court interpretations explicitly barred intentional discrimination, federal agencies historically implemented broader protections through agency regulations. Shortly after the law’s passage, HHS—then operating as the Department of Health, Education, and Welfare—alongside other federal agencies, adopted regulations that prohibited disparate-impact discrimination. Disparate impact refers to standard policies, criteria, or operating procedures that, while appearing neutral on their face, generate a disproportionately adverse effect on individuals belonging to a protected class based on race, color, or national origin. These long-standing regulations were grounded in the recognition that seemingly neutral administrative practices could inadvertently perpetuate, reinforce, or severely exacerbate systemic inequities in access to public benefits, health services, and medical treatment.
In the realm of modern health care, disparate impacts often arise from deeply embedded institutional policies and historical practices, even as overt, intentional discrimination has grown less common. For instance, historical housing policies such as redlining continue to exert measurable residual effects today, driving the residential segregation of Black and Hispanic populations into urban neighborhoods that frequently suffer from depleted infrastructure, fewer health resources, and elevated environmental health risks. Within clinical medicine itself, disproven assumptions regarding biological differences across racial categories have persisted, occasionally permeating clinical decision-making, diagnostic algorithms, treatment guidelines, and medical tools.
Furthermore, language barriers within health systems have long been recognized as a major driver of unequal care. Inadequate language assistance services can severely delay a patient’s ability to obtain timely diagnosis and treatment, contribute to preventable medical errors, foster patient dissatisfaction, and ultimately lead to poor chronic disease management and worse clinical outcomes. For more than fifty years, federal civil rights authorities relied upon disparate-impact regulations to investigate, scrutinize, and resolve these types of structural barriers among recipients of federal funds.
Disparate-impact standards have historically shaped comprehensive federal guidance issued to healthcare providers and program administrators. For example, HHS previously issued extensive guidance regarding individuals with limited English proficiency (LEP), establishing that healthcare providers could violate Title VI if their operational criteria had the discriminatory effect of limiting national origin groups’ meaningful access to care. These principles were similarly embedded in the Office of Minority Health’s National Culturally and Linguistically Appropriate Services Standards. During the height of the COVID-19 pandemic, the HHS Office for Civil Rights issued specialized guidance warning that Title VI applied to vaccine distribution methods that could inadvertently yield disparate impacts. The guidance noted that requirements to obtain vaccines exclusively through online appointment portals or remote pharmacy locations could disproportionately depress vaccination rates in communities of color, prompting agencies to advise providers to proactively identify and eliminate structural, linguistic, and geographic barriers.
Under the newly enacted 2026 final rule, however, disparate impact is entirely eliminated as an independent administrative basis for enforcing Title VI under HHS regulations. Moving forward, HHS will exclusively initiate enforcement actions and compliance investigations when there is affirmative evidence of intentional discrimination based on race, color, or national origin. Consequently, under the revised regulatory framework, a policy, procedure, or institutional practice that disproportionately harms a protected group is no longer sufficient, on its own, to establish a formal violation of Title VI.
HHS has defended the regulatory changes by asserting that they bring agency rules into strict alignment with the literal text of Title VI, longstanding Supreme Court jurisprudence, and Executive Order 14281. The final rule clarifies that while statistical evidence demonstrating stark racial or ethnic disparities may still be submitted or reviewed as background context during an investigation, these disparities alone cannot legally establish unlawful discrimination without accompanying proof of discriminatory intent.
This shift alters how HHS handles civil rights complaints, narrowing the federal government’s authority to proactively review institutional policies that yield unintended disproportionate consequences. Without the threat of disparate-impact liability, healthcare providers, insurers, and other federally funded entities face fewer federal administrative pressures to audit their operational algorithms, digital scheduling platforms, facility locations, and language access protocols for unintended exclusionary effects.
Because federal disparate-impact enforcement under Title VI has been dismantled, stakeholders are examining alternative legal avenues at both the federal and state levels. Certain protections remain available under other statutes, though their scope, jurisdiction, and application vary widely. For instance, Section 1557 of the Affordable Care Act continues to prohibit discrimination in covered health programs based on race, color, national origin, sex, age, and disability, and it maintains specific mandates concerning language access. Nevertheless, the administration has signaled forthcoming adjustments to Section 1557 implementing regulations as well.
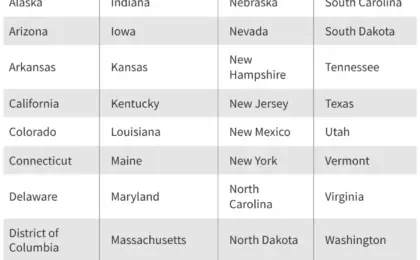
At the state level, mechanisms to address health disparities differ significantly. Some states maintain independent statutory protections against discriminatory effects. In California, state law explicitly prohibits discrimination in state-funded programs across a broad array of protected characteristics, with implementing regulations that maintain a state-level disparate impact standard comparable to the one recently removed from federal HHS rules. Similarly, Illinois enacted the Civil Rights Safeguard Act, which broadens state-level protections against disparate-impact discrimination across employment, financial credit, and public accommodations, including healthcare settings.
However, because these safeguards are localized rather than universal, the elimination of the federal standard means that the legal protections available to patients facing structural and systemic inequities will depend heavily on their geographic location.








No comments yet. Be the first to join the conversation!