
The Medicare program continues to serve as a critical lifeline for more than 70 million Americans, providing essential health insurance coverage to older adults ages 65 and older, as well as younger adults living with long-term disabilities. While the federal program covers a broad spectrum of necessary health care services, beneficiaries routinely face significant financial responsibilities. Participants generally pay out-of-pocket for their monthly premiums, annual deductibles, and various cost-sharing requirements for Medicare-covered services. Recent years have seen a steady upward trajectory in these expenses, with projections indicating that costs will continue to climb over the coming decade.
This financial reality intersects with the modest economic circumstances of a substantial portion of the Medicare population. Data indicates that one in four Medicare beneficiaries lived on incomes below $24,600 per person in 2024. Furthermore, out-of-pocket spending on premiums and cost-sharing expenses consumed more than a third—specifically 36 percent—of the average beneficiary’s Social Security income in 2023.
The financial burden a beneficiary experiences can vary widely depending on the coverage pathway they choose. Individuals eligible for Medicare can receive their benefits either through traditional Medicare or by enrolling in a privately administered Medicare Advantage plan. Those who choose traditional Medicare can supplement their coverage by signing up for prescription drug benefits through a stand-alone Part D plan and may also purchase a Medicare supplemental insurance policy, commonly known as Medigap, to help manage out-of-pocket medical expenses.
Conversely, Medicare Advantage plans typically bundle prescription drug coverage directly into the package and establish annual limits on out-of-pocket spending for Medicare-covered services—a feature traditional Medicare lacks. However, these private plans often require enrollees to receive care within a specified network of providers, imposing higher costs or denying coverage entirely for out-of-network services. Because each coverage option entails distinct premium structures, cost-sharing rules, and substantial plan-to-plan variation, navigating the marketplace can be remarkably complex. The financial impact can be especially heavy for beneficiaries who require high levels of health care.
Premiums for Medicare Part A and Part B
For the vast majority of participants, Medicare Part A—which covers inpatient hospital stays, short-term nursing facility care, hospice, and certain home health services—requires a monthly premium of $0. Individuals generally qualify for premium-free Part A if they or their spouse worked and paid Medicare payroll taxes for at least 40 quarters, translating to 10 years of employment. Those who are otherwise eligible for Medicare but fall short of this work history requirement may still enroll by paying a monthly premium. In 2026, the Part A premium is set at $311 per month, or $3,732 annually, for beneficiaries with between 30 and 39 quarters of covered employment. For individuals with fewer than 30 quarters of employment, the monthly premium rises to $565, or $6,780 for the year.
A late enrollment penalty applies to individuals who are required to pay a Part A premium but delay their enrollment beyond their initial eligibility window without qualifying group health coverage in the interim. This penalty increases the monthly Part A premium by 10 percent and remains in effect for twice the number of years enrollment was delayed. For instance, a person with 30 quarters of covered employment who delayed enrollment for two years would incur the penalty until 2029, paying $342.10 per month for Part A coverage in 2026.
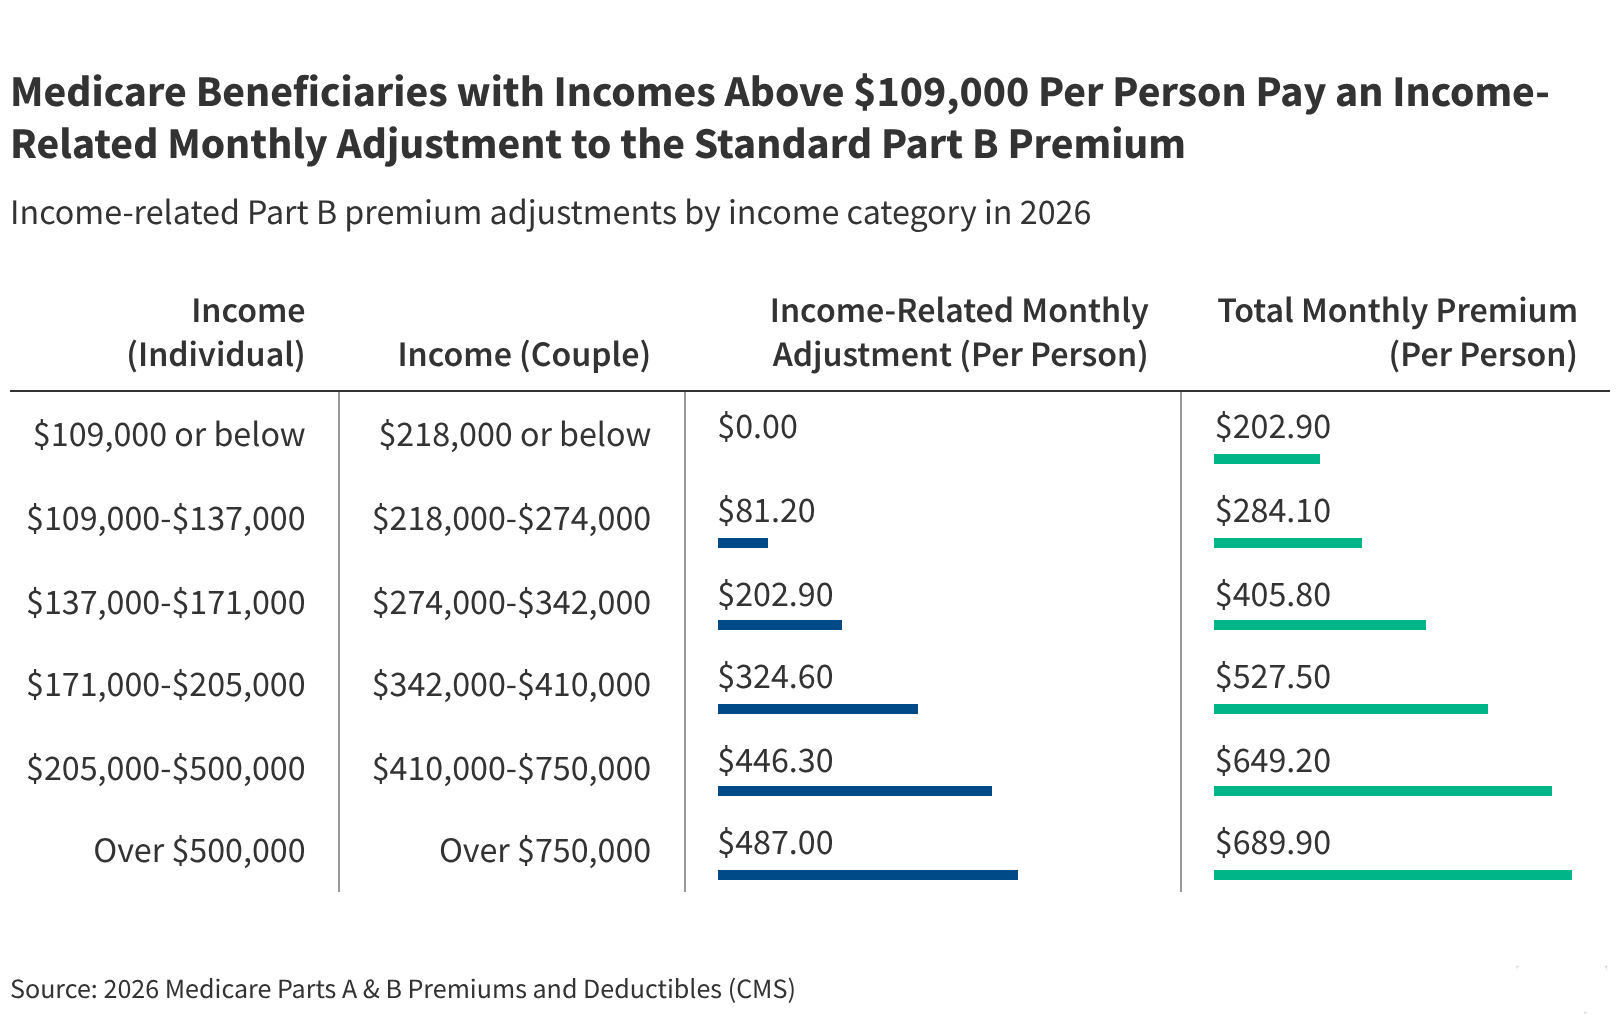
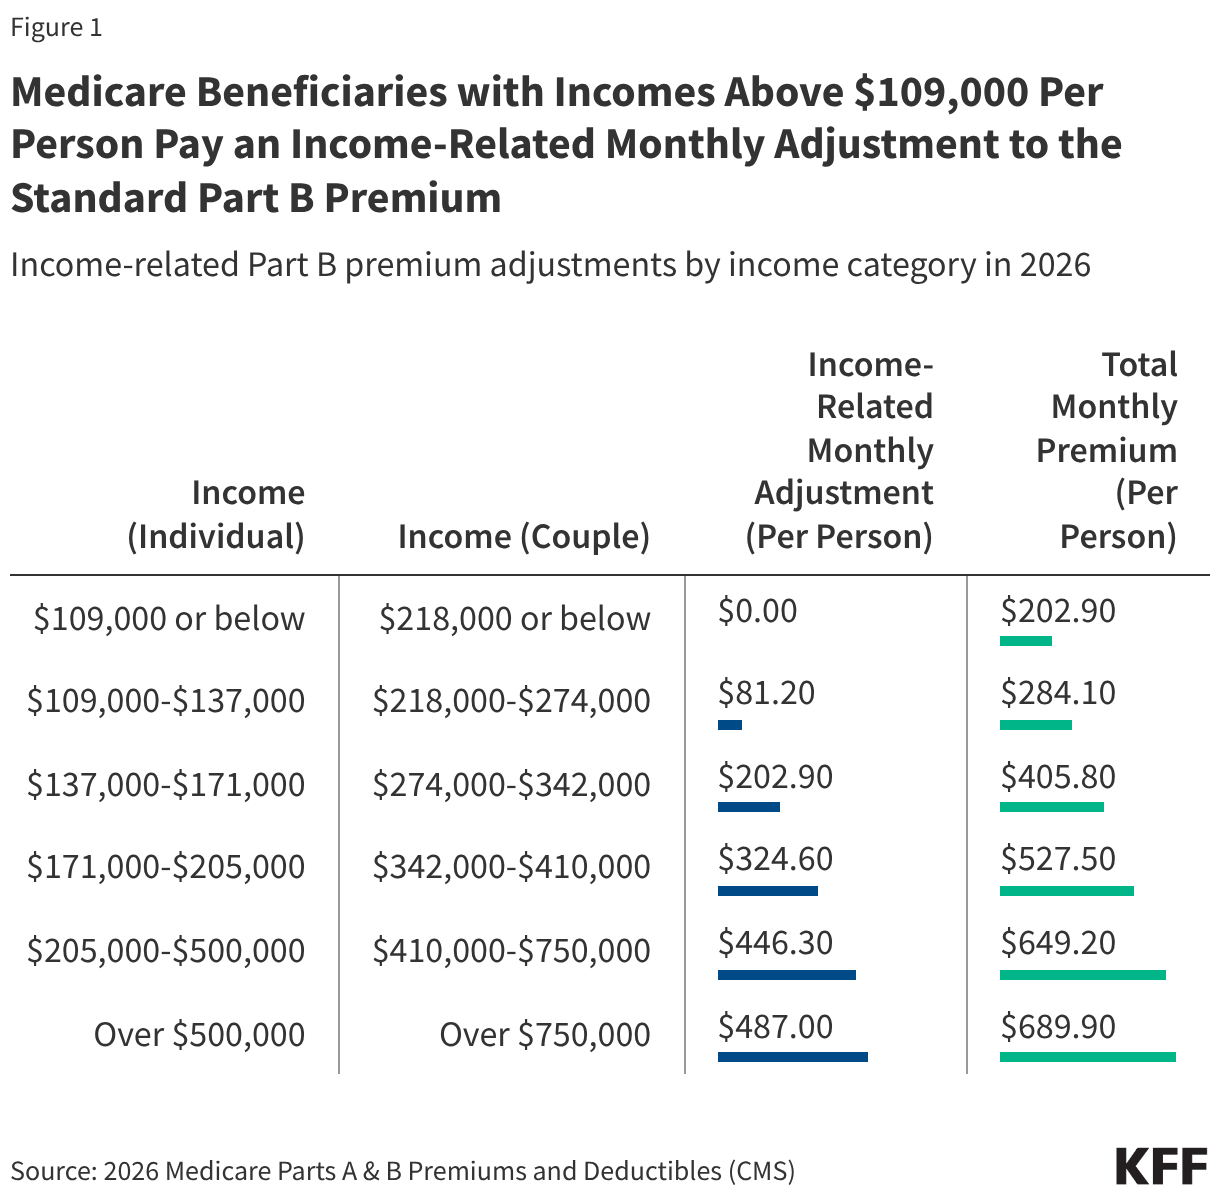
In contrast, monthly premiums are mandatory for Medicare Part B regardless of whether a beneficiary is enrolled in traditional Medicare or a Medicare Advantage plan. Part B covers essential outpatient services, including physician visits, preventive care, diagnostic tests, outpatient hospital procedures, and physician-administered drugs. The standard Part B premium stands at $202.90 per month, or $2,434.80 annually. Beneficiaries with higher incomes face income-related monthly adjustment amounts that push their premiums higher. Individuals with incomes exceeding $109,000, or married couples earning more than $218,000, pay an income-adjusted Part B premium ranging from $284.10 to $689.90 per person per month. Beneficiaries with limited incomes and modest assets may qualify for assistance from their state Medicaid program to help cover these premium costs.
Similar to Part A, failing to enroll in Part B during the initial enrollment period without qualifying group coverage results in a permanent late enrollment penalty. This penalty adds 10 percent to the standard monthly premium for each full 12-month period that enrollment was delayed. For example, a two-year delay results in a 20 percent monthly penalty, bringing the individual’s monthly Part B premium to $243.48.
Cost-Sharing Requirements in Traditional Medicare
Within traditional Medicare, cost sharing for Part A inpatient hospital services involves a deductible of $1,736 per benefit period rather than a calendar year. This means a beneficiary hospitalized multiple times throughout the year may be required to pay the deductible more than once. Additional cost sharing begins after the first 60 days of a continuous hospital stay, requiring payments of $434 per day for days 61 through 90, and $868 per day for each additional day thereafter up to a lifetime reserve cap of 60 days.
For skilled nursing facility care following a qualifying hospital stay, beneficiaries pay no cost sharing for the first 20 days, followed by a daily charge of $217 for days 21 through 100. Once a beneficiary reaches the 100-day limit per benefit period, they assume full financial responsibility for any further care. Other Part A offerings, such as hospice and home health services, generally carry no deductibles or coinsurance, though modest cost sharing may apply to specific items like respite care or pain management medications.
Part B services in traditional Medicare operate under an annual deductible of $283, alongside a standard coinsurance rate of 20 percent for approved medical services, doctor visits, mental health care, and durable medical equipment. Crucially, a wide array of preventive services—such as annual wellness visits, standard immunizations, mammograms, and certain cancer screenings—are exempt from both deductibles and coinsurance.
Because traditional Medicare does not cap annual out-of-pocket spending for Part A and Part B services, many beneficiaries opt to purchase Medigap supplemental policies. These private insurance policies help cover deductibles and coinsurance, shielding beneficiaries from catastrophic medical bills. Medigap policyholders pay a separate monthly premium to their insurer in addition to their Part B premium. The average premium for Medigap coverage was $217 per month in 2023, though these rates vary widely by age, state, and policy type. Other avenues for supplemental assistance include employer-sponsored retirement coverage and state Medicaid programs, which can assist low-income beneficiaries with both premiums and out-of-pocket expenses.
Costs Under Medicare Advantage
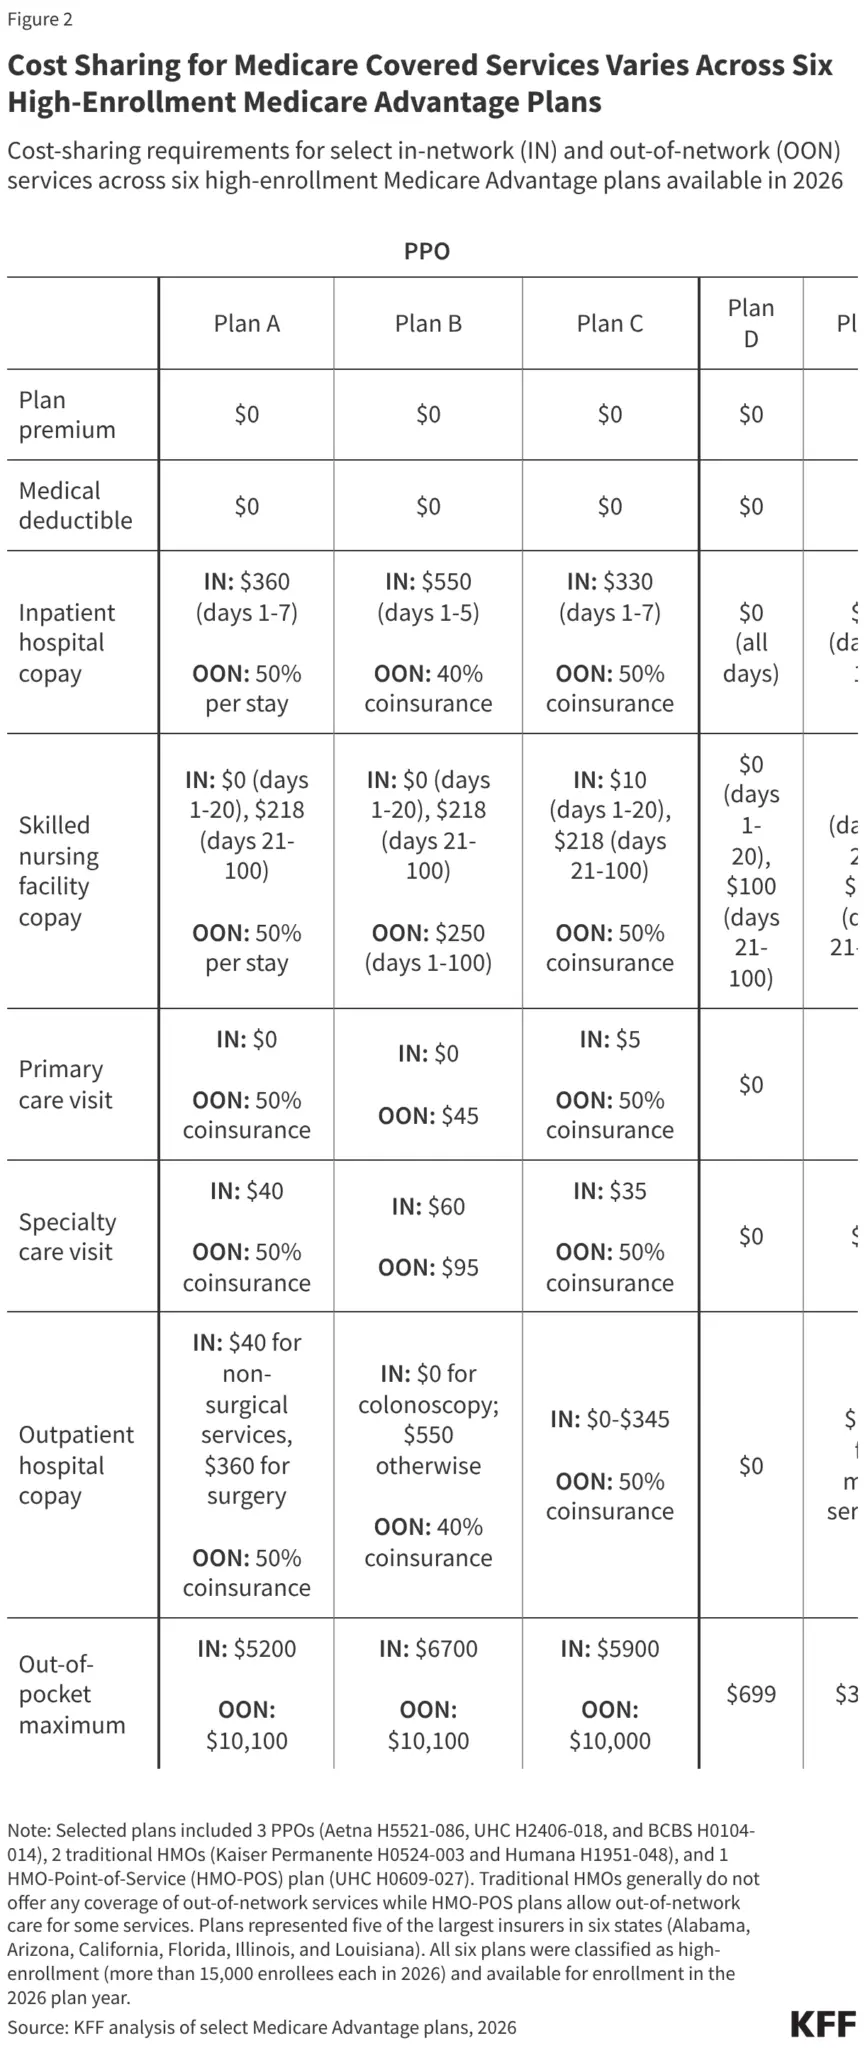
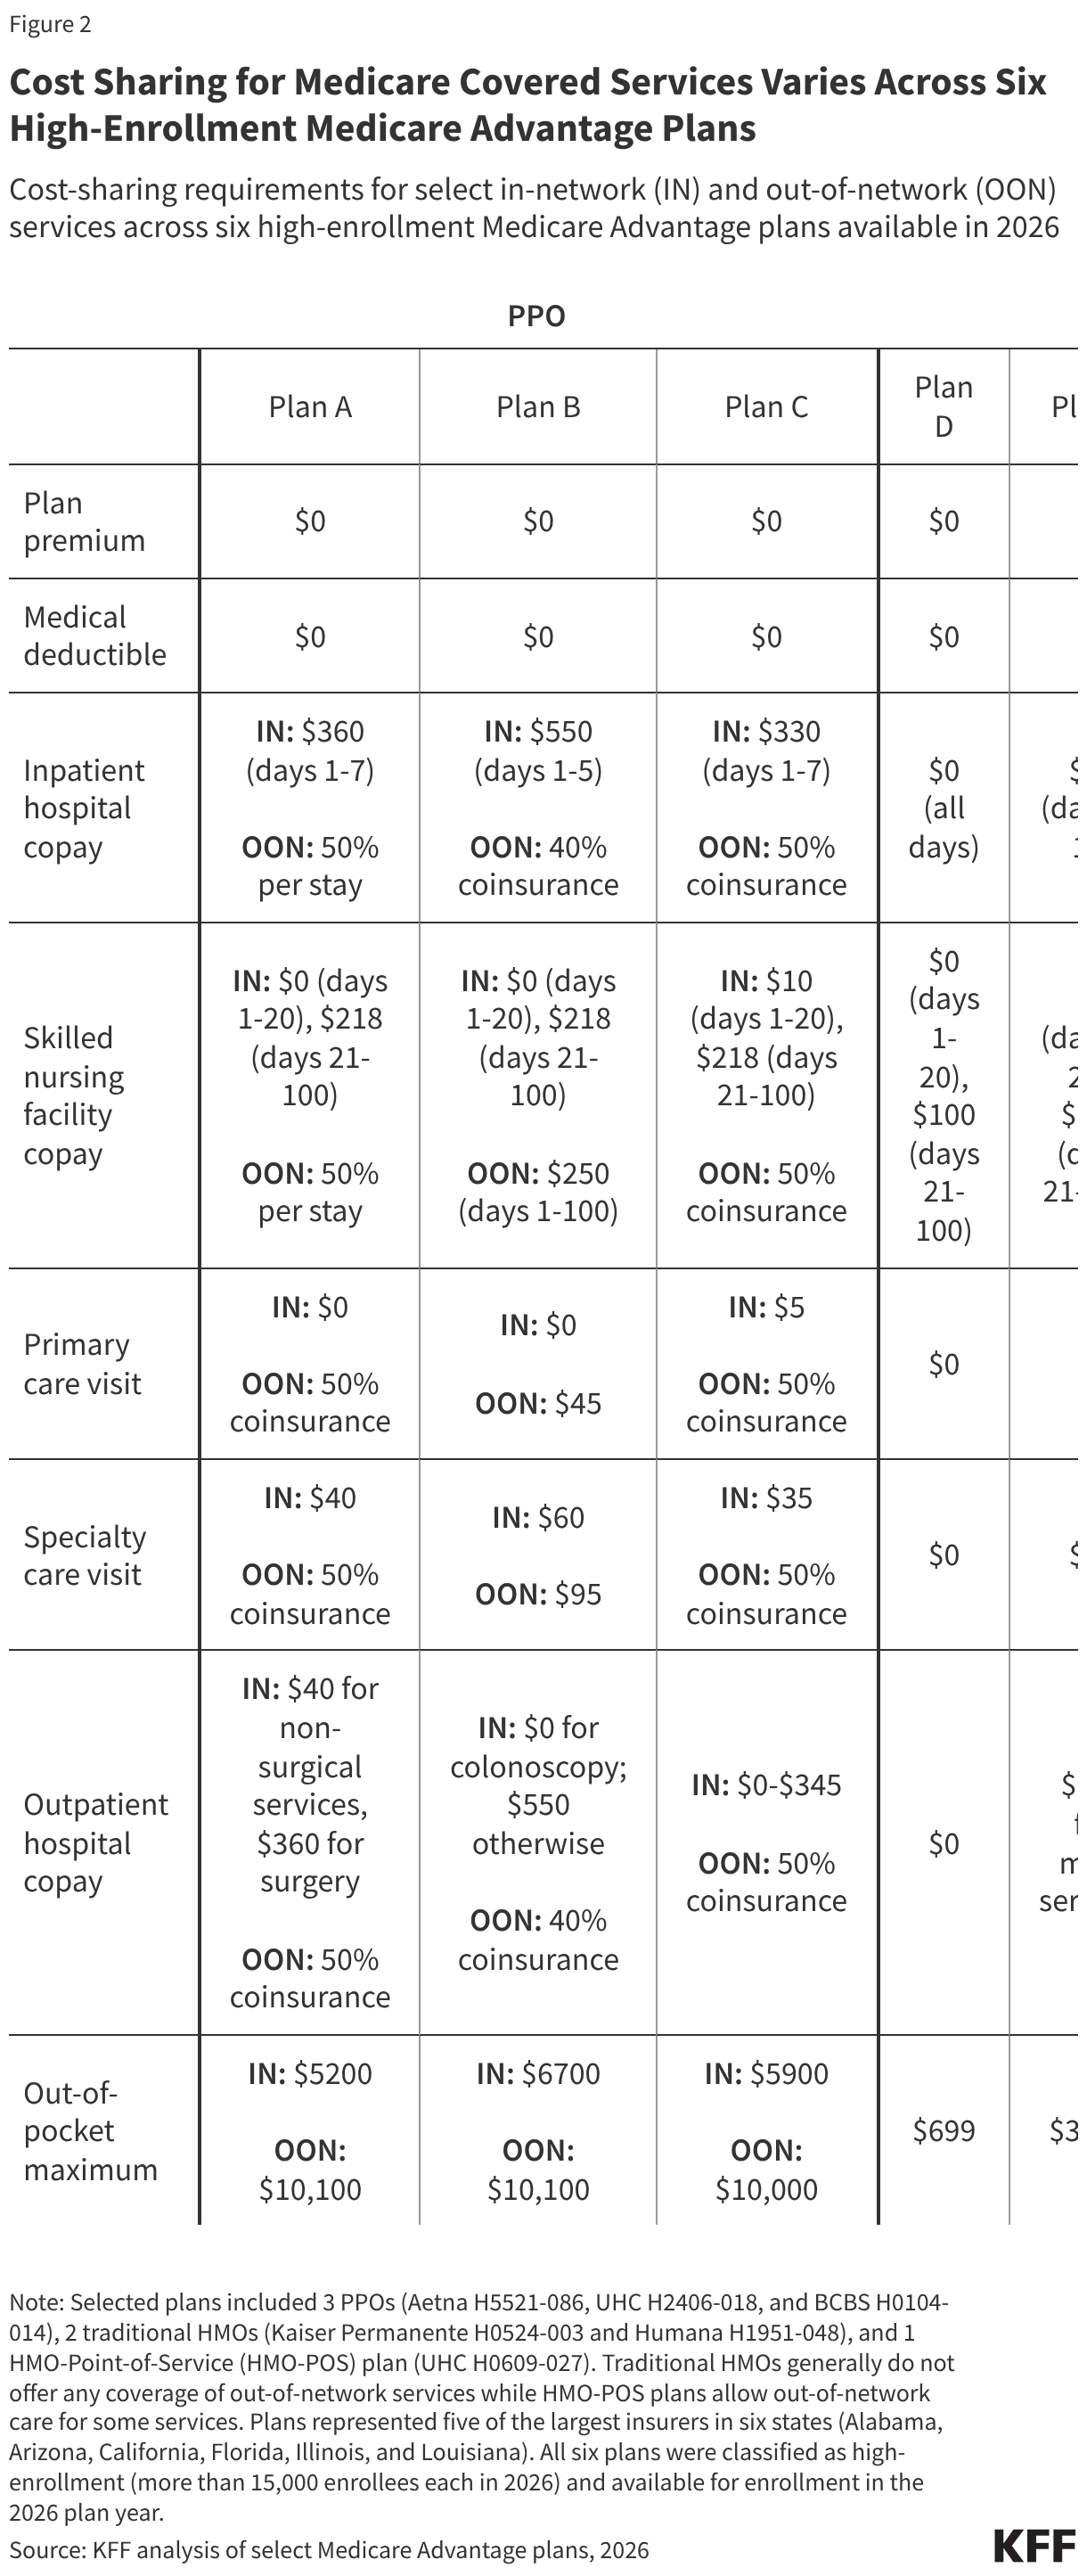
Medicare Advantage plans serve as a private alternative to traditional Medicare, bundling Part A and Part B benefits while typically incorporating prescription drug coverage and supplemental benefits such as routine dental, vision, and hearing care. While these plans often feature lower cost-sharing requirements for individual services, they frequently utilize provider networks, referrals, and prior authorization protocols to manage care utilization.
While enrollees must continue paying the standard Part B premium—and the Part A premium if they lack work history—the vast majority of Medicare Advantage participants pay no additional plan premium. Among plans that include prescription drug coverage, the enrollment-weighted average premium is $15 per month, heavily influenced by the fact that 75 percent of enrollees choose zero-premium plans. Furthermore, roughly one-third of enrollees are in plans that utilize federal rebate funds to reduce a portion of their monthly Part B premium, typically by less than $10.
Although specific cost-sharing amounts vary significantly across different plans and provider networks, Medicare Advantage plans are legally required to establish a ceiling on annual out-of-pocket spending. In 2026, these spending caps cannot exceed $9,250 for in-network services or $13,900 for combined in-network and out-of-network services, though many plans enforce much lower limits. The average out-of-pocket limit sits at $5,421 for in-network services across all plan types, and $9,825 for combined services within Preferred Provider Organization plans.
Costs for Part D Prescription Drug Coverage
Medicare Part D provides outpatient prescription drug coverage through private plans, either as stand-alone prescription drug plans or integrated within Medicare Advantage packages. Monthly premiums, formularies, pharmacy networks, and deductibles vary extensively across the marketplace.
While many Part D enrollees pay a monthly premium, the average cost for a stand-alone plan is $36 per month. For those enrolled in Medicare Advantage drug plans, the drug coverage portion averages $8 per month, with three-quarters of individual plan enrollees paying no separate premium. Higher-income beneficiaries are subject to income-related monthly adjustments ranging from $14.50 to $91.00 added to their base plan premium. Conversely, low-income beneficiaries meeting specific asset and income criteria can access financial assistance through the Part D Low-Income Subsidy program, which minimizes or eliminates deductibles, copayments, and premiums.
A late enrollment penalty applies to individuals who go without creditable prescription drug coverage for 63 consecutive days or more after their initial enrollment window closes. This penalty adds a permanent monthly fee equal to 1 percent of the base beneficiary premium for every month of delayed coverage.
The standard Part D deductible is set at $615, though individual plans frequently offer enhanced structures with lower or eliminated deductibles. Cost sharing generally involves a tiered system combining flat copayments and coinsurance rates that vary depending on whether a drug is generic, a preferred brand, a non-preferred option, or a specialty medication.
Crucially, out-of-pocket spending for all Part D enrollees is capped at $2,100. Once a beneficiary reaches this spending threshold, they incur no additional costs for covered medications for the remainder of the calendar year. Enrollees also retain the option to spread their out-of-pocket expenses across the calendar year to maintain more manageable monthly budgets.









No comments yet. Be the first to join the conversation!